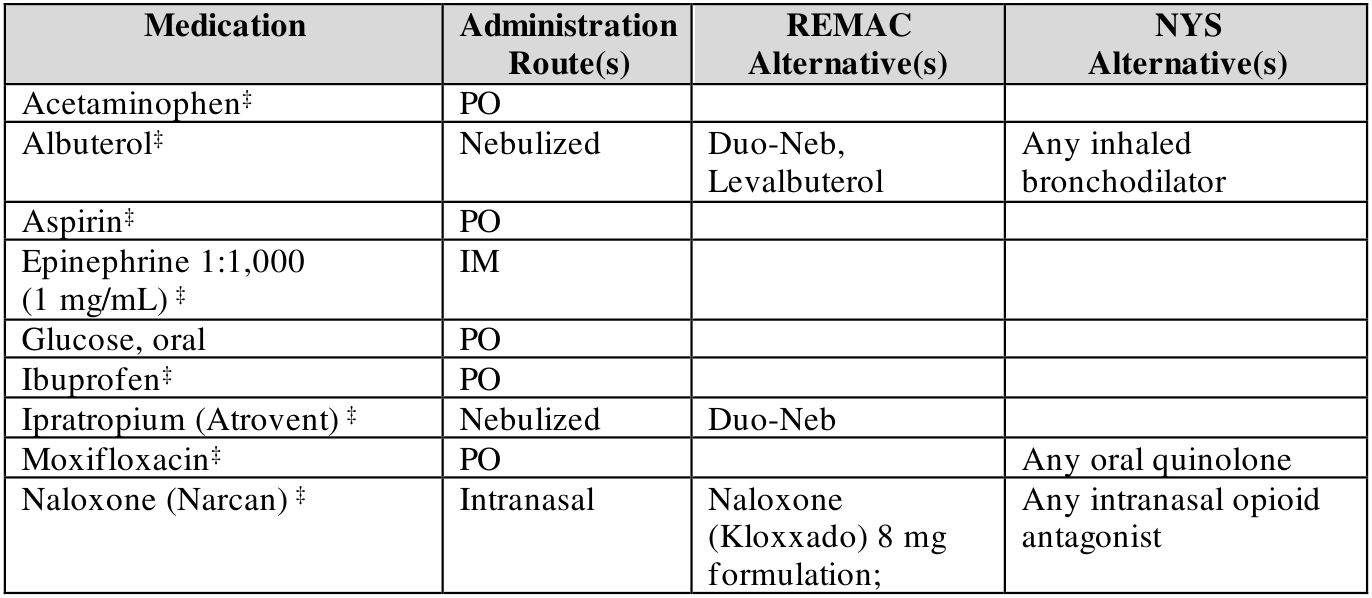
- Minimum quantities of medications shall be determined by the respective REMAC.
- Included in this formulary are any optional medications (Signified by ‡ ) that may be used pursuant to these protocols if equipped and trained, and may be subject to REMAC authorization.
- Also included are medications that may be used as an alternative in cases of temporary shortage or unavailability. Any use of a “REMAC Alternative” medication requires REMAC approval and Bureau of EMS notification and is intended to be temporary while awaiting availability.
- Any desire to use a “NYS Alternative” requires REMAC approval of the desired medication and written request and approval by the New York State Bureau of EMS and Trauma prior to use. Again, such alternatives are intended to be temporary while awaiting availability.
- Any use of an alternative requires the agency to identify the drug, dose, route, replacement indication and contraindications and provide training on the medication to its practitioner’s that is approved in advance by the respective REMAC.