Environmental: Hypothermia
Applies to adult and pediatric patients
Criteria
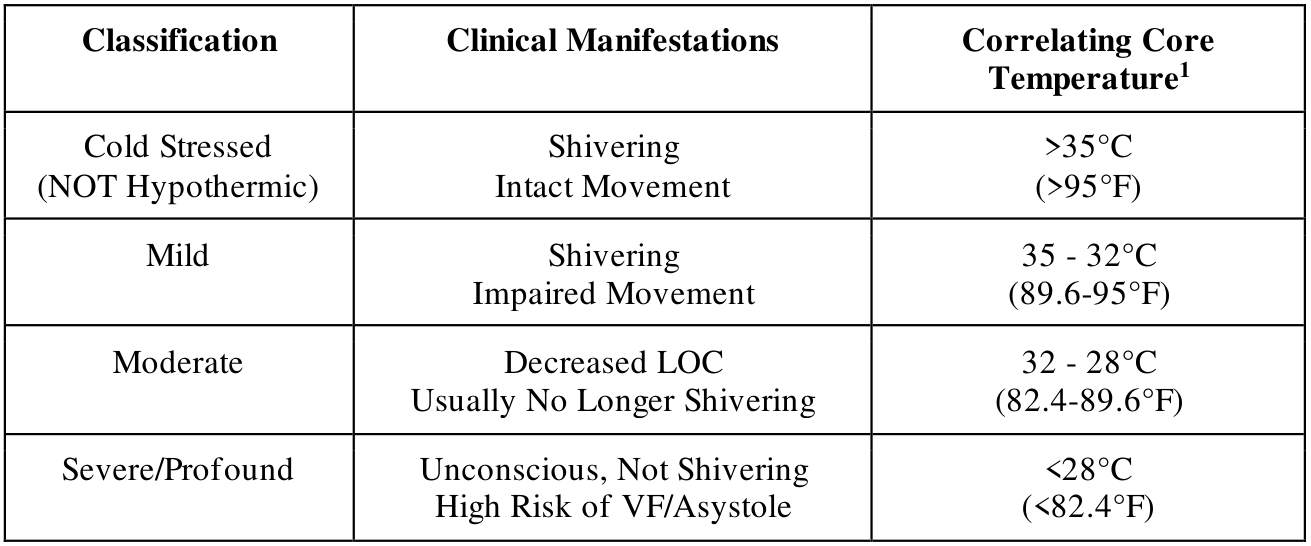
- This protocol does not apply to cold stressed patients as these patients are not hypothermic
All levels
- Mild Hypothermia:
- Handle gently
- Remove wet clothing once moved into a warm environment
- Provide insulation² (blankets)
- Provide vapor barrier³, if available (plastic tarp or mylar sheets)
- Heat inside of the ambulance
- Moderate Hypothermia:
- Treat for mild hypothermia and
- Minimize movement during extrication (NO standing or walking)
- Attempt to maintain the patient in a horizontal position
- Begin active external rewarming:
- Apply heat sources to axilla, chest, and back; place a thin barrier between heat source & skin to avoid thermal burns⁴
- Assess skin frequently for any signs of impending burns
- Severe/Profound Hypothermia:
- Treat for Moderate hypothermia and
- In patients with no signs of life:
- Assess pulse and breathing for 60 seconds⁵
- If no pulse or breathing, begin standard cardiac arrest resuscitation, see “Cardiac Arrest: General Approach”
- Limit AED to one shock, if indicated
- Rigor mortis, fixed pupils, & dependent lividity are not obvious signs of death in a hypothermic patient
- Obvious signs of death include trauma inconsistent with life or extensive chest wall rigidity that interferes with the ability to perform chest compressions
Medical control
- Patients with severe/profound hypothermia, hemodynamic instability, or cardiac arrest may benefit from transport to a facility capable of performing extracorporeal life support (ECLS) if available and <1-hour transport; facilities with cardio-pulmonary bypass capabilities may be an alternative if transport times are significant
Key points
- 1 Core temperatures are for reference only and refer to esophageal temperature monitoring
- 2 Insulating material includes clothing, blankets, sleeping bags, insulated pads, etc.
- 3 Common vapor barriers include tarps, plastic sheets, reflective blankets, commercial emergency blankets
- 4 Avoid using non-medical heat packs (e.g., those commonly used for hand and foot warming) as they do not provide sufficient surface area to warm the patient effectively but increase the probability of thermal burns due to high surface temperature
- 5 Heart and respiratory rates may be slow and difficult to detect in hypothermia
- A hypothermic patient meeting trauma center criteria should be transported to a trauma center
- Pulse oxygenation measurement may be inaccurate if the patient is hypothermic. If the patient is cyanotic and in respiratory distress, administer oxygen.
- Perform a complete examination to assess potential causes of altered mental status other than hypothermia
- Classification of hypothermia should be based on clinical manifestations. Oral temperature readings are inaccurate in hypothermic states while bladder and rectal temperatures can lag behind esophageal temperatures by up to one hour.